FDA announces voluntary recall of valsartan of some company following detection of an impurity

The U.S. Food and Drug Administration is alerting health care professionals and patients of a voluntary recall of several drug products containing the active ingredient valsartan, used to treat high blood pressure and heart failure. This recall is due to an impurity, N-nitrosodimethylamine (NDMA), which was found in the recalled products. However, not all products containing valsartan are being recalled. NDMA is classified as a probable human carcinogen (a substance that could cause cancer) based on results from laboratory tests. The presence of NDMA was unexpected and is thought to be related to changes in the way the active substance was manufactured.

The FDA’s review is ongoing and has included investigating the levels of NDMA in the recalled products, assessing the possible effect on patients who have been taking them and what measures can be taken to reduce or eliminate the impurity from future batches produced by the company.

There are currently three voluntary recalls related to the NDMA impurity detected in the valsartan API:

  • Teva Pharmaceuticals USA labeled as Major Pharmaceuticals — recall is at the retail level because these products are only used in facilities where they are directly administered to patients by health care professionals: Valsartan 80 mg and 160 mg products
  • Prinston Pharmaceuticals Inc. labeled as Solco Healthcare LLC — recall is at the consumer/user level: Valsartan 40 mg, 80 mg, 160 mg, and 320 mg; and valsartan/HCTZ 80 mg/12.5 mg, 160 mg/12.5 mg, 160 mg/25 mg, 320 mg/12.5 mg, and 320 mg/25 mg products
  • Teva Pharmaceuticals labeled as Actavis LLC — recall is at the consumer/user level: Valsartan 40 mg, 80 mg, 160 mg, and 320 mg; and valsartan/HCTZ 80 mg/12.5 mg, 160 mg/12.5 mg, 160 mg/25 mg, 320 mg/12.5 mg, and 320 mg/25 mg products.


BACKGROUND: Valsartan is used to treat high blood pressure and heart failure. Not all products containing valsartan are being recalled. This update will clarify which valsartan-containing products are being recalled.

The recalled products contain an impurity, N-nitrosodimethylamine (NDMA), in the API manufactured by Zhejiang Huahai Pharmaceuticals, Linhai, China. The presence of the potentially cancer-causing NDMA was unexpected, and the agency believes the NDMA is related to changes in the way the active substance was manufactured. Some levels of the impurity may have been in the valsartan-containing products for as long as four years.

RECOMMENDATION: Patients should be aware that not all valsartan-containing medications are affected and being recalled and if you have questions, you should ask your pharmacist or health care provider. Patients should:

  • compare the information on your prescription bottle with the information in this list (company, National Drug Code, lot number) to determine if your current medicine has been recalled.
  • continue taking your current medicine until your health care provider or pharmacist gives you a replacement or a different treatment option.

Health professionals should know:

  • FDA has determined the recalled valsartan products pose an unnecessary risk to patients. Therefore, FDA recommends patients use valsartan-containing medicines made by other companies or consider other available treatment options for the patient’s medical condition.

 

Tecovirimat is the First Drug for the Treatment of Smallpox

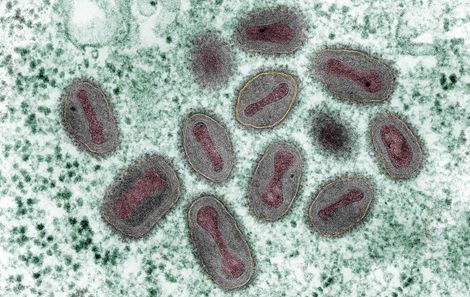
The U.S. Food and Drug Administration today approved TPOXX (tecovirimat), the first drug with an indication for treatment of smallpox. Though the World Health Organization declared smallpox, a contagious and sometimes fatal infectious disease, eradicated in 1980, there have been longstanding concerns that smallpox could be used as a bioweapon.

“To address the risk of bioterrorism, Congress has taken steps to enable the development and approval of countermeasures to thwart pathogens that could be employed as weapons. Today’s approval provides an important milestone in these efforts. This new treatment affords us an additional option should smallpox ever be used as a bioweapon,” said FDA Commissioner Scott Gottlieb, M.D. “This is the first product to be awarded a Material Threat Medical Countermeasure priority review voucher. Today’s action reflects the FDA’s commitment to ensuring that the U.S. is prepared for any public health emergency with timely, safe and effective medical products.”

Prior to its eradication in 1980, variola virus, the virus that causes smallpox, was mainly spread by direct contact between people. Symptoms typically began 10 to 14 days after infection and included fever, exhaustion, headache and backache. A rash initially consisting of small, pink bumps progressed to pus-filled sores before finally crusting over and scarring. Complications of smallpox could include encephalitis (inflammation of the brain), corneal ulcerations (an open sore on the clear, front surface of the eye) and blindness.

TPOXX’s effectiveness against smallpox was established by studies conducted in animals infected with viruses that are closely related to the virus that causes smallpox, and was based on measuring survival at the end of the studies. More animals treated with TPOXX lived compared to the animals treated with placebo. TPOXX was approved under the FDA’s Animal Rule, which allows efficacy findings from adequate and well-controlled animal studies to support an FDA approval when it is not feasible or ethical to conduct efficacy trials in humans.

The safety of TPOXX was evaluated in 359 healthy human volunteers without a smallpox infection. The most frequently reported side effects were headache, nausea and abdominal pain.

The FDA granted this application Fast Track and Priority Review designations. TPOXX also received Orphan Drug designation, which provides incentives to assist and encourage the development of drugs for rare diseases and a Material Threat Medical Countermeasure Priority Review Voucher, which provides additional incentives for certain medical products intended to treat or prevent harm from specific chemical, biological, radiological and nuclear threats.

The FDA granted approval of TPOXX to SIGA Technologies Inc.

TPOXX was developed in conjunction with the U.S. Department of Health and Human Services’ Biomedical Advanced Research and Development Authority (BARDA).

Preconception blood pressure predicts risk of pregnancy loss

Healthy young women with elevations in preconception blood pressure (BP) appear to be at increased risk of pregnancy loss, according to a study.

Researchers evaluated preconception BP in relation to reproductive outcomes such as fecundability, pregnancy loss and live birth in 1,228 women (mean age 28.7 years) attempting to conceive with a history of pregnancy loss.

Systolic and diastolic BP were taken during the first observed menstrual cycle and in early pregnancy, with the resulting measurements used to obtain mean arterial pressure. Fecundability was assessed using human chorionic gonadotropin testing. Pregnancy loss included both human chorionic gonadotropin–detected and clinical losses.

Mean preconception systolic and diastolic BP were 111.6 and 72.5 mm Hg, respectively. Elevations in diastolic BP and mean arterial pressure were associated with a heightened risk of pregnancy loss. Specifically, the risk increased by 18 percent (95 percent CI, 1.03–1.36) per 10-mm Hg increase in diastolic BP and by 17 percent (1.02–1.35) per 10-mm Hg increase in mean arterial pressure. Results were similar for early pregnancy BP.

In contrast, preconception BP was not associated with fecundability or live birth.

The present data indicate that preconception BP is a marker of increased risk of pregnancy loss, independent of age, body mass index and other risk factors. They also contribute to the evidence base suggesting that early markers of cardiometabolic risk may be associated with adverse reproductive events, researchers said.

Lifestyle interventions targeting BP elevations during preconception may reduce the risk of pregnancy loss, a particular concern among women with a history of pregnancy loss, they added. Increasing physical activity and following a DASH-type (Dietary Approaches to Stop Hypertension) diet may favourably affect reproductive health and reduce future risk of cardiovascular disease among reproductive-aged women.

Dupilumab safe & effective for Atopic Dermatitis

Dupilumab, at dose regimens of 300 mg once weekly (qw) or once every 2 weeks (q2w), is effective and safe for atopic dermatitis, a recent meta-analysis has shown.

Pooled analysis of six trials (n=2,447) revealed that there was a significant decrease in the Eczema Area and Severity Index (EASI) scores following dupilumab treatment.

The effect remained significant in both the 300 mg qw (SMD, –0.93; –1.10 to –0.76; p<0.00001) and q2w (SMD, –0.86; –1.02 to –0.71; p<0.00001) dosing regimens.

Dupilumab was better than placebo even when using other efficacy measures: percentage of body surface area (SMD, –0.83; –0.90 to –0.75; p<0.00001), Investigators Global Assessment response (risk ratio [RR], 3.82; 3.23–4.51; p<0.00001), pruritus numeric rating scale score (SMD, –0.81; –0.96 to –0.66; p<0.00001) and Dermatology Life Quality Index (SMD, –0.78; –0.89 to –0.66; p<0.00001).

In all cases above, both dosing regimens were significantly effective.

Ceftazidime & Avibactam for the Treatment of Patients with Hospital-Acquired & Ventilator-Associated Bacterial Pneumonia

Certain types of Gram-negative bacteria have become increasingly resistant to available antibiotics, resulting in increased illness and death as well as contributing to escalating healthcare costs.1 New strategies to fight these challenging infections have been long-awaited by the medical community.

“Healthcare providers in the U.S. have not had access to a new treatment option for patients with HABP/VABP due to Gram-negative bacteria in over 15 years,” said David Nicholson, Ph.D., Chief Research and Development Officer, Allergan. “Gram-negative pathogens are some of the most pressing antibiotic resistance threats and cause more than 40,000 resistant infections in the U.S. annually. Today’s action by the FDA is further evidence of Allergan’s commitment to improving outcomes and meeting critical needs in patients with life-threatening infectious diseases.”

This is the third therapeutic indication for Avycaz. Avycaz was first approved in February 2015 in the U.S. for the treatment of adult patients with complicated intra-abdominal infections (cIAI), in combination with metronidazole, and in 2017 for complicated urinary tract infections (cUTI), including pyelonephritis, caused by designated susceptible Gram-negative bacteria, including certain Enterobacteriaceae and Pseudomonas aeruginosa.

“Clinical efficacy along with patient safety are critical priorities to clinicians managing serious Gram-negative bacterial infections. We are thrilled to have a new option available to treat HABP/VABP, some of the most challenging Gram-negative infections in the hospital setting,” said Jose Vazquez, M.D., FIDSA, Division Chief and Professor of Medicine Infectious Diseases, Medical College of Georgia/Augusta University, Augusta, GA.

Hospital-Acquired Bacterial Pneumonia/Ventilator-Associated Bacterial Pneumonia (HABP/VABP)

Hospital-acquired bacterial pneumonia (HABP) and ventilator-associated bacterial pneumonia (VABP) are serious bacterial infections that occur in hospitalized patients, which are associated with critically ill and vulnerable populations. The Gram-negative bacteria that commonly cause HABP/VABP include the Enterobacteriaceae (including Klebsiella penumoniae, Escherichia coli, Enterobacter cloacae, Proteus mirabilis) and Pseudomonas aeruginosa.

The economic burden associated with HABP/VABP is significant. These infections are associated with increased healthcare costs, high morbidity and mortality, and lengthened hospital stays. HABP/VABP is currently the second most common type of nosocomial infection in the U.S., especially in the intensive care unit (ICU) of hospitals.2

About Avycaz

Avycaz is a fixed-dose combination antibacterial indicated for the treatment of HABP/VABP, cIAI (in combination with metronidazole), and cUTI caused by designated susceptible Gram-negative microorganisms in patients 18 years or older. Avycaz consists of a combination of avibactam and ceftazidime.

Avibactam is a first-in-class non-beta-lactam beta-lactamase inhibitor which protects ceftazidime against degradation by certain beta-lactamases. Avibactam does not decrease the activity of ceftazidime against ceftazidime-susceptible organisms. Ceftazadime is a third-generation cephalosporin with a well-established efficacy and safety profile.

Avycaz has demonstrated in vitro activity against Enterobacteriaceae in the presence of some beta-lactamases and extended-spectrum beta-lactamases (ESBLs) of the following groups: TEM, SHV, CTX-M, Klebsiella pneumoniae carbapenemase (KPCs), AmpC and certain oxacillinases (OXA). Avycaz also demonstrated in vitro activity against Pseudomonas aeruginosa in the presence of some AmpC beta-lactamases, and certain strains lacking outer membrane porin (OprD). Avycaz is not active against bacteria that produce metallo-beta lactamases and may not have activity against Gram-negative bacteria that overexpress efflux pumps or have porin mutations.

Ceftazidime and avibactam is being jointly developed with Pfizer. Allergan holds the rights to commercialize ceftazidime and avibactam in North America under the brand name Avycaz, while Pfizer holds the rights to commercialize the combination in the rest of the world under the brand name ZAVICEFTA®.

INDICATIONS AND USAGE

Hospital-acquired Bacterial Pneumonia and Ventilator-associated Bacterial Pneumonia (HABP/VABP)

Avycaz (ceftazidime and avibactam) is indicated for the treatment of hospital-acquired bacterial pneumonia and ventilator-associated bacterial pneumonia (HABP/VABP) caused by the following susceptible Gram-negative microorganisms: Klebsiella pneumoniae, Enterobacter cloacae, Escherichia coli, Serratia marcescens, Proteus mirabilis, Pseudomonas aeruginosa, and Haemophilus influenzae in patients 18 years or older.

Complicated Intra-Abdominal Infections (cIAI)

Avycaz, in combination with metronidazole, is indicated for the treatment of complicated intra-abdominal infections (cIAI) caused by the following susceptible Gram-negative microorganisms: Escherichia coli, Klebsiella pneumoniae, Proteus mirabilis, Enterobacter cloacae, Klebsiella oxytoca, Citrobacter freundii complex, and Pseudomonas aeruginosa in patients 18 years or older.

Complicated Urinary Tract Infections (cUTI), including Pyelonephritis

Avycaz is indicated for the treatment of complicated urinary tract infections (cUTI) including pyelonephritis caused by the following susceptible Gram-negative microorganisms: Escherichia coli, Klebsiella pneumoniae, Enterobacter cloacae, Citrobacter freundii complex, Proteus mirabilis, and Pseudomonas aeruginosa in patients 18 years or older.

Metformin May Up Survival in Older Men With Moderate CKD

Veterans who developed type 2 diabetes and who were started on monotherapy with metformin rather than a sulfonylurea had a lower risk of dying up to 6 years later — whether their kidney function was normal or mild to moderately impaired, in a new study.

The study excluded patients with severe chronic kidney disease (CKD), defined as estimated glomerular filtration rate (eGFR) < 30 mL/min/1.73 m2.

Of note, patients with moderate CKD (eGFR 30–44 mL/min/1.73m2) who received metformin as opposed to a sulfonylurea had an even greater absolute benefit than patients with better kidney function.

“This is a population in which evidence regarding the health benefits of metformin is limited,” say Zachary A Marcum, PharmD, PhD, from the University of Washington, Seattle, and colleagues in their recent paper in the Journal of General Internal Medicine.

These findings, together with results from previous studies, support the FDA’s guidance from April 2016 “to consider metformin initiation among individuals with an eGFR of 45–59 mL/min/ 1.73 m2 [mild CKD]” and suggests that “metformin initiation may be beneficial among persons” with even worse kidney function (ie, moderate CKD), they note.

“What we’re seeing here is further evidence of metformin’s benefit in individuals with diabetes and CKD,” Dr Marcum told Medscape Medical News.

However, “it’s too soon to say that the FDA should change” the labeling requirement for metformin, since the current findings need to be replicated in other populations,” he added.

Mortality With Metformin vs Sulfonylurea in Diabetes Plus CKD

When metformin was approved by the FDA in 1995, it was contraindicated in patients with higher serum creatinine levels, due to fears of lactic-acid acidosis, which had been seen with another drug in the same class, phenformin, Dr Marcum and colleagues explain.

Vitamin D Supplements May Make Arteries Healthier

High doses of vitamin D seem to keep arteries more flexible and pliable, potentially warding off future heart disease, heart attacks and strokes, preliminary research suggests.

In just four months, vitamin D supplements reduced arterial stiffness in a group of 70 young black men and women, according to results from a small-scale clinical trial.

The flexibility of participants’ arteries improved even more with higher doses of vitamin D, said senior researcher Dr. Yanbin Dong, a professor with the Medical College of Georgia at Augusta University, in Augusta.

“Their arterial stiffness decreased, and the more vitamin D, the better,” Dong said.

Vitamin D is known to be essential for bone health, but for the past couple of decades scientists have suspected it might be important in other ways, he said.

“The vitamin D receptor is expressed everywhere in your body, in almost every single type of cell,” Dong said. “That’s why people think vitamin D might have something more to offer.”

To see if the vitamin might improve the health of blood vessels, Dong and his colleagues recruited a group of overweight or obese black Americans who were deficient in vitamin D.

Human skin naturally synthesizes vitamin D when exposed to bright sunshine. However, darker skin absorbs less sunlight, making black people more susceptible to vitamin deficiency, the researchers said.

In addition, body fat tends to capture and hold vitamin D, also contributing to deficiency.

The study participants were placed into four groups. Three groups took oral doses of vitamin D amounting to 600 international units (IU), 2,000 IU or 4,000 IU daily. The fourth group took inactive placebos.

The National Academy of Medicine currently recommends that people get 600 IU of vitamin D daily, Dong said. The researchers chose 2,000 IU because they suspected that might be the best dose, and 4,000 IU because that’s the highest level before people start experiencing toxic effects.

Also, previous studies have shown that, taken daily, 2,000 IU and 4,000 IU doses of vitamin D can bring a vitamin-deficient person’s levels of vitamin D back within a normal range, the study authors noted.

Those in the study who took 4,000 IU daily — more than six times the currently recommended amount — experienced a 10.4 percent reduction in arterial stiffness within four months, the findings showed.

Those who took 2,000 IU a day experienced a 2 percent decrease in arterial stiffness during the same timeframe. People who took the currently recommended dose of 600 IU had a slight increase in arterial stiffness — about 0.1 percent. Those who took the placebos had a 2.3 percent increase, according to the report.

No toxic effects were observed among people who took the larger doses of the vitamin, Dong said.

Vitamin D might help arterial health by blocking a hormone system that increases constriction of blood vessels, the researchers said. It also helps reduce inflammation, which has been linked to hardened arteries.

Dong expects that some whites also would benefit from vitamin D supplementation.

“We expect we would see similar effects in white people who have similar vitamin D deficiency and are overweight,” he said.

However, taking handfuls of vitamin D will not excuse a person from eating right or exercising for their heart health, Dong added.

“I don’t think vitamin D should be an alternative for any other lifestyle modifications,” Dong said. “We need to exercise, we need to eat sensibly. Vitamin D is just like anything else. It could be helpful on top of those things. It cannot replace.”

These findings, however, present an opportunity to ward off heart disease in younger people at high risk, said Dr. Robert Eckel, director of the University of Colorado Hospital’s Lipid Clinic.

Hardening of the arteries tends to be irreversible in older people who already have large amounts of arterial plaque as well as health problems such as diabetes and high cholesterol, Eckel said. This study, though, focused mainly on people in their 20s, he noted.

“Looking at vitamin D earlier in life — before there’s a lot of cardiovascular disease on board — could be an encouraging improvement,” said Eckel, who was not involved with the new study. “We’re talking about primary prevention here.”

The study participants should be tracked to see if their more flexible arteries translate to lower rates of heart disease and stroke later in life, Eckel said. Future trials should also examine the effects of vitamin D on other races and ethnic groups, he said.

The study was published online recently in the journal PLOS One.

First Nebulized LAMA Inhaler for COPD

The US Food and Drug Administration (FDA) has approved glycopyrrolate inhalation solution 25 mcg twice daily (Lonhala Magnair, Sunovion Pharmaceuticals) for maintenance treatment of airflow obstruction in adults with chronic obstructive pulmonary disease (COPD), including chronic bronchitis and/or emphysema.

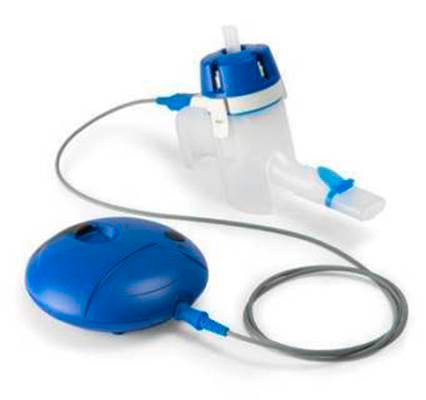
Lonhala Magnair is the first nebulized long-acting muscarinic antagonist (LAMA) approved by the FDA for the treatment of COPD. It is the first time the Magnair eFlow technology system, developed by PARI Pharma GmbH, has been used, Sunovion said in a news release.

“This technology is a virtually silent, portable, closed system nebulizer that is designed to deliver the drug in two to three minutes and allows people to breathe normally while using the device,” the company said.

“Despite the availability of several therapies, many people still struggle to control their COPD ― a challenge that may be affected by the delivery method used to administer a medication,” Gary Ferguson, MD, of the Pulmonary Research Institute of Southeast Michigan in Farmington Hills, said in the release.

“Lonhala Magnair offers an important new option that combines the efficacy of a proven medication for COPD with the attributes of a unique handheld nebulizer that allows a person to breathe normally while taking their medication,” Dr Ferguson said.

The approval is based on data from the clinical trials in the GOLDEN (Glycopyrrolate for Obstructive Lung Disease via Electronic Nebulizer) program, which included GOLDEN-3 and GOLDEN-4, two phase 3 randomized, double-blind, placebo-controlled studies in adults with moderate to very severe COPD.

In these studies, individuals using Lonhala Magnair showed “statistically significant and clinically important” changes from baseline in trough forced expiratory volume in 1 second (FEV1) at 12 weeks, the company said.

In addition, the GOLDEN-5 phase 3 study demonstrated the long-term safety and tolerability of Lonhala Magnair in comparison with tiotropium bromide delivered by the HandiHaler device in adults with moderate to very severe COPD. Overall, treatment-emergent adverse events were similar for patients receiving glycopyrrolate and those receiving tiotropium during a 48-week period, the company said.

Sunovion expects to be available in US pharmacies in early 2018.

Lonhala Magnair should not be started in patients with acutely deteriorating COPD or to relieve sudden symptoms of COPD and should not be used more than twice daily. It is contraindicated in patients with hypersensitivity to glycopyrrolate or any of the ingredients.

Once-Weekly Bydureon BCise (exenatide) for Patients with Type-2 Diabetes

FDA approves new treatment for pediatric patients with type 2 diabetes

AstraZeneca today announced that the US Food and Drug Administration (FDA) has approved Bydureon® BCise™ (exenatide extended-release) injectable suspension, a new formulation of Bydureon (exenatide extended-release) injectable suspension in an improved once-weekly, single-dose autoinjector device for adults with type-2 diabetes whose blood sugar remains uncontrolled on one or more oral medicines in addition to diet and exercise, to improve glycemic control.

Unlike other glucagon-like peptide-1 (GLP-1) receptor agonists, Bydureon BCise has a unique, continuous-release microsphere delivery system designed to provide consistent therapeutic levels of the active ingredient, exenatide, to help patients reach and maintain steady state. The new formulation in the innovative Bydureon BCise device is proven to reduce blood sugar levels, with the added benefit of weight loss, although not a weight loss medicine.

Across two clinical trials, average HbA1c reductions of up to 1.4% and average weight loss of up to 3.1 pounds were achieved when used as monotherapy or as an add-on to metformin, a sulfonylurea, a thiazolidinedione, or any combination of two of these oral anti-diabetic medicines at 28 weeks. The most common adverse reactions reported in ≥5% of patients in clinical trials were nausea (8.2%) and adverse events associated with injection-site nodules (10.5%).

Bydureon BCise is designed for ease and patient convenience in a once-weekly, pre-filled device with a pre-attached hidden needle. The medication is administered in three simple steps – mix, unlock, inject.

Ruud Dobber, President, AstraZeneca US and Executive Vice President, North America, said: “We know that physicians have established longstanding confidence in the significant HbA1c reduction Bydureon provides their patients to help achieve consistent control, with the added benefit of weight loss. With the approval of Bydureon BCise, we’re now introducing a new formulation in an improved, easy-to-use device, that will help enhance the patient experience.”

Bydureon BCise will be available for patients in the US in the first quarter of 2018. Bydureon Pen will also remain available for patients. A regulatory application for the new autoinjector device has also been accepted by the European Medicines Agency.

Secnidazole for Bacterial Vaginosis

The US Food and Drug Administration (FDA) last week approved an antibiotic called secnidazole (Solosec, Symbiomix Therapeutics) for women with bacterial vaginosis.

Secnidazole is the first single-dose oral treatment for bacterial vaginosis, the most common vaginal infection in women aged 15 to 44 years, according to the Centers for Disease Control and Prevention.

A dose of secnidazole comes in the form of a 2-g packet of granules. Patients sprinkle the granules on applesauce, yogurt, or pudding and eat the mixture within 30 minutes without chewing or crunching the granules.

Most current antibiotics for bacterial vaginosis must be taken for 5 to 7 days, and often more than once a day. As a single-dose treatment, secnidazole promises to improve adherence and the likelihood of a cure, Symbiomix Therapeutics stated in a news release.

The FDA determined that secnidazole was safe and effective on the basis of two randomized, placebo-controlled clinical trials involving 333 nonpregnant women up to age 54 years.

Vulvovaginal candidiasis, headache, nausea, dysgeusia, vomiting, and diarrhea were among the most common adverse events observed in the two studies. The drug’s label warns that vulvovaginal candidiasis associated with the use of secnidazole may require treatment with an antifungal drug.

The agency also warns about the potential risk for carcinogenicity because mice and rats treated chronically with drugs structurally related to secnidazole have developed tumors.

“Avoid chronic use.”

The drug is not recommended for women who are breast-feeding. If they take it, however, they should discontinue breast-feeding for 96 hours afterward.