Shockwave Lithoplasty for Peripheral Vascular Disease

SEPTEMBER 19TH, 2016

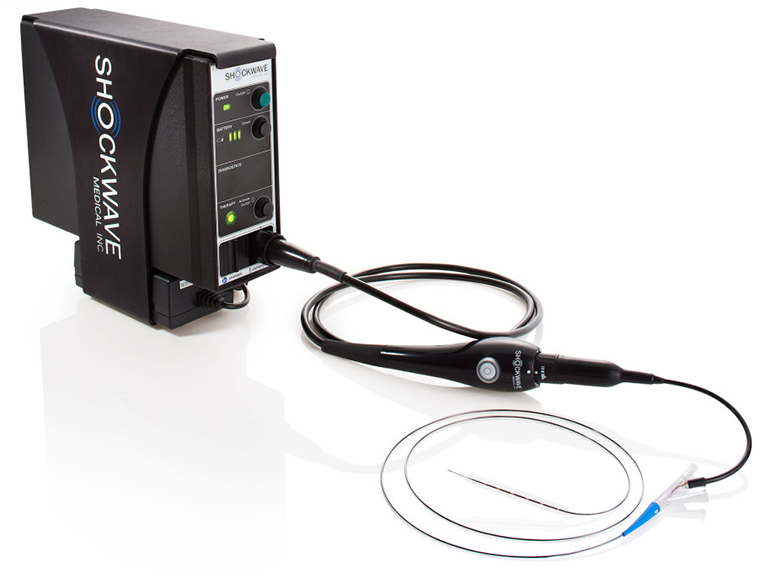
A unique system that uses a balloon and sound waves to break up plaque in patients with peripheral artery disease has just been cleared by the FDA. The Lithoplasty system from Shockwave, a firm out of Fremont, California, is basically a traditional angioplasty balloon catheter with added capability that resembles lithotripsy that’s used to break up kidney stones.

The transducers along the length of the balloon section are tuned to generate sound at frequencies that resonate hardened calcium. Being all shook up, the calcium deposits are motivated to crack and to allow the balloon to push them closer to the vessel wall. This results in a wider lumen and should lead to improved outcomes for patients with peripheral artery disease for whom an extra millimeter or two of increased space for blood to flow can make a whole lot of difference.

“Lithoplasty represents a new mechanism of treatment and is revolutionary for the care of patients with calcified peripheral vascular disease, a difficult-to-treat patient population,” in a statement said Kenneth Rosenfield, M.D., Section Head for Vascular Medicine and Intervention at Massachusetts General Hospital. “Existing devices for treating these patients have significant shortcomings that make it challenging to successfully open arteries, while minimizing vascular injury and complications. Lithoplasty is a unique approach that allows us to successfully treat these diseased vessels using a device built on a familiar balloon catheter platform, while minimizing the risk of vessel injury, including dissections that require stenting or other additional interventions.”

Canagliflozin/Metformin Hydrochloride Extended-Release for the Treatment of Adults with Type 2 Diabetes

September 21, 2016 – Janssen Pharmaceuticals, Inc. (Janssen) announced today the U.S. Food and Drug Administration (FDA) has approved Invokamet XR – a once-daily, fixed-dose combination therapy of canagliflozin and metformin hydrochloride extended-release (XR)—for first-line use as an adjunct to diet and exercise to improve blood glucose control in adults with type 2 diabetes when treatment with the two medications is appropriate.[1] Invokamet XR combines Invokana (canagliflozin), the most prescribed sodium glucose co-transporter 2 (SGLT2) inhibitor, with more than 9 million U.S. prescriptions since launch,[2] and an XR formulation of metformin. Metformin is commonly prescribed as an initial therapy for the treatment of type 2 diabetes.

“Invokamet XR offers the convenience of once-daily dosing and provides physicians needed flexibility for tailoring treatment to the needs of type 2 diabetes patients, especially those with higher A1C levels,” said John Anderson, M.D.,* Frist Clinic, Nashville, Tenn. “As with Invokamet, physicians can prescribe the XR formulation to adults when they are first diagnosed with type 2 diabetes or as additional therapy for people whose A1C levels are not well controlled with either agent alone.”

Phase 3 studies have shown the combination of Invokana and metformin reduces A1C significantly more than metformin alone, sitagliptin plus metformin, or glimepiride plus metformin. Treatment with Invokana as an add-on to metformin also demonstrated greater reductions in the secondary endpoints of body weight and systolic blood pressure.

The approved indication for Invokamet XR aligns with current type 2 diabetes treatment guidelines from the American Association of Clinical Endocrinologists and American College of Endocrinology and from the American Diabetes Association, which recommend dual therapy for patients with higher A1C levels.[3],[4] Specifically, guidelines recommend dual therapy for patients who have an initial A1C level of 7.5 percent or higher[3] and for those who have an initial level below 7.5 percent and do not achieve an A1C treatment goal after about three months on single therapy, often metformin.4 In addition, dual or triple therapy is recommended as first-line therapy in asymptomatic patients with an initial A1C level above 9 percent.[3]

A1C is a measure of average blood glucose over the past two to three months; the American Diabetes Association recommends most adults with type 2 diabetes maintain A1C levels of 7 percent or less.[5]

“The approval of Invokamet XR is further evidence of our ongoing commitment to provide new treatment options for people with type 2 diabetes,” said Paul Burton, M.D., Ph.D., Vice President, Medical Affairs, Janssen. “Our Invokana portfolio now offers physicians even more choices for helping patients improve control of A1C levels and other important health measures, with numerous dosing options for monotherapy and for combination therapy with both metformin and metformin XR.”

Invokamet XR is available in four dosages, in tablets containing canagliflozin 50 milligrams (mg) or 150 mg, and metformin XR 500 mg or 1000 mg. The recommended dosing is two tablets once daily with the morning meal. The prescribing information for Invokamet XR also contains a boxed warning for lactic acidosis, a rare but serious complication that can occur due to metformin accumulation.[1]

Studies in healthy adults have demonstrated that administration of Invokamet XR results in the same levels of canagliflozin and metformin XR in the body as when corresponding dosages of the two medicines are administered as separate tablets. Canagliflozin works with the kidneys to help adults with type 2 diabetes lose some sugar through the process of urination, and metformin decreases the production of glucose in the liver and improves the body’s response to insulin. Invokamet XR should not be used in patients with type 1 diabetes or for the treatment of diabetic ketoacidosis.[1]

Invokamet, the first combination of an SGLT2 inhibitor and an immediate-release formulation of metformin available in the United States, was initially approved by FDA in August 2014 as an adjunct to diet and exercise to improve glycemic control in adults with type 2 diabetes not adequately controlled with metformin or canagliflozin, or who are already being treated with both medications separately. In May 2016, FDA expanded the Invokamet indication to include adults with type 2 diabetes who are not already being treated with canagliflozin or metformin and may benefit from dual therapy.


Increased thyroid function associated with higher dementia risk

High and high-normal thyroid function is associated with increased risk of dementia, experts say.

Data analysis was done within the Rotterdam Study. A total of 9,446 subjects with a mean age of 65 years were included in the evaluation of the link between thyroid-stimulating hormone (TSH) and free thyroxine with dementia, cognition, and subclinical vascular brain disease by MRI. The subjects were followed-up for a mean duration of 8 years. During this period, 601 subjects developed dementia.

In both full and normal ranges of thyroid function, high TSH function was associated with dementia risk, independent of cardiovascular risk factors.

Subjects with higher free thyroxine were at greater risk of developing dementia. High TSH in older women was associated with decreased absolute 10-year dementia risk.

An association was seen between higher TSH and better global cognitive scores while thyroid function was not linked with to subclinical vascular brain disease.

The authors concluded that high and high-normal thyroid function may increase the risk of developing dementia.

Eteplirsen for Duchenne Muscular Dystrophy

September 19, 2016 — The U.S. Food and Drug Administration today approved Exondys 51 (eteplirsen) injection, the first drug approved to treat patients with Duchenne muscular dystrophy (DMD). Exondys 51 is specifically indicated for patients who have a confirmed mutation of the dystrophin gene amenable to exon 51 skipping, which affects about 13 percent of the population with DMD.

“Patients with a particular type of Duchenne muscular dystrophy will now have access to an approved treatment for this rare and devastating disease,” said Janet Woodcock, M.D., director of the FDA’s Center for Drug Evaluation and Research. “In rare diseases, new drug development is especially challenging due to the small numbers of people affected by each disease and the lack of medical understanding of many disorders. Accelerated approval makes this drug available to patients based on initial data, but we eagerly await learning more about the efficacy of this drug through a confirmatory clinical trial that the company must conduct after approval.”

DMD is a rare genetic disorder characterized by progressive muscle deterioration and weakness. It is the most common type of muscular dystrophy. DMD is caused by an absence of dystrophin, a protein that helps keep muscle cells intact. The first symptoms are usually seen between three and five years of age, and worsen over time. The disease often occurs in people without a known family history of the condition and primarily affects boys, but in rare cases it can affect girls. DMD occurs in about one out of every 3,600 male infants worldwide.

People with DMD progressively lose the ability to perform activities independently and often require use of a wheelchair by their early teens. As the disease progresses, life-threatening heart and respiratory conditions can occur. Patients typically succumb to the disease in their 20s or 30s; however, disease severity and life expectancy vary.

Exondys 51 was approved under the accelerated approval pathway, which provides for the approval of drugs that treat serious or life-threatening diseases and generally provide a meaningful advantage over existing treatments. Approval under this pathway can be based on adequate and well-controlled studies showing the drug has an effect on a surrogate endpoint that is reasonably likely to predict clinical benefit to patients (how a patient feels or functions or whether they survive). This pathway provides earlier patient access to promising new drugs while the company conducts clinical trials to verify the predicted clinical benefit.

The accelerated approval of Exondys 51 is based on the surrogate endpoint of dystrophin increase in skeletal muscle observed in some Exondys 51-treated patients. The FDA has concluded that the data submitted by the applicant demonstrated an increase in dystrophin production that is reasonably likely to predict clinical benefit in some patients with DMD who have a confirmed mutation of the dystrophin gene amenable to exon 51 skipping. A clinical benefit of Exondys 51, including improved motor function, has not been established. In making this decision, the FDA considered the potential risks associated with the drug, the life-threatening and debilitating nature of the disease for these children and the lack of available therapy.

Can Stress Lower a Woman’s Fertility?

Sept. 20, 2016 — New research seems to confirm that stress lowers a woman’s chances of becoming pregnant, particularly stress that occurs around the time of ovulation.

“If you are feeling more stress than you usually do [around ovulation time], you are 40 percent less likely to get pregnant that month,” said study author Kira Taylor. She is an assistant professor of epidemiology and population health at the University of Louisville School of Public Health and Information Sciences.

Taylor believes her team’s study is the first to look at stress at different time periods in a woman’s monthly cycle, to determine if there are different effects at different points.

In the study, the researchers evaluated 400 women, aged 40 and younger. All were sexually active and not using contraception.

“Only about a third were actively trying to get pregnant, but all were having unprotected sex, without birth control,” Taylor said.

On a daily basis, the women recorded their stress levels, from one (lowest) to four (highest). They did so for up to 20 cycles, or until pregnancy occurred. On average, the women recorded their stress for eight cycles.

Over the study period, 139 women became pregnant. There was a 46 percent reduction in conception for each one-unit rise in stress during the ovulation window, the researchers found. Day 14 of the cycle was estimated as the time of ovulation.

The impact on conceiving held even after the investigators took into account other factors, such as age, body mass index (a measurement based on weight and height), alcohol use and how often sex occurred.

The researchers looked at other times in the cycle as well, but “we did not find an effect of stress on implantation,” Taylor said. “Implantation generally occurs six to 10 days after ovulation, if you have conceived.”

While the study found a connection between stress and conception, it didn’t prove cause and effect.

In another finding, “women who did get pregnant had much higher levels [of stress] around the end of their cycle.” Taylor said that may be due to hormone levels, with increasing levels of estrogen and progesterone causing mood swings at that time.

Dr. Tomer Singer, director of reproductive endocrinology and infertility at Lenox Hill Hospital in New York City, said the new research pinpoints the time period most affected by stress.

“They were able to focus a light on the important time of being stress-free, and this is the first half of the [cycle],” he said.

Taylor’s team did not look at why stress affected conception at the time of ovulation. But, she speculated that “stress disrupts the signaling between the brain and the ovaries, and reduces the chances of ovulation.”

Singer agreed. He said when a woman has a high stress level, hormones responsible for ovulation can be disrupted.

This hormonal disruption can hamper the process, Taylor said, so “it could be nature’s way of saying ‘Don’t have a baby right now.’ ”

Singer suggested that women can reduce their stress levels by practicing yoga or mindfulness meditation, among other ways.

Moderate exercise, five times a week for 30 minutes, can also reduce stress, Taylor said. But exercising to extremes can reduce the likelihood of conceiving, she said.

She also suggested that using talk therapy and time-management skills could lower stress levels.

The study was published online recently in the Annals of Epidemiology.

Tenofovir prevents hepatitis B transmission in pregnancy

The use of tenofovir disoproxil fumarate (TDF) during pregnancy resulted in lower rate of mother-to-child transmission of hepatitis B virus (HBV) compared with those who received usual care without antiviral therapy, a recent study finds.

To assess the efficacy of TDF use during pregnancy for the prevention of HBV transmission from mother to child, researchers randomized 197 mothers who were positive for hepatitis B e antigen (HBeAg) and who had an HBV DNA level higher than 200,000 IU per millilitre to receive usual care without antiviral therapy (n=100) or TDF (n=97; 300 mg/day) from 30 to 32 weeks of gestation until postpartum week 4. The participants were followed until postpartum week 28. All the infants received immunoprophylaxis.

The primary outcomes were the rates of mother-to-child transmission and birth defects. The secondary outcomes were the safety of TDF, the percentage of mothers with an HBV DNA level of less than 200,000 IU per milliliter at delivery, and loss or seroconversion of HBeAg or hepatitis B surface antigen at postpartum week 28.

At delivery, 68 percent of the mothers in the TDF group, as compared with 2 percent in the control group (2 of 100), had an HBV DNA level of less than 200,000 IU per milliliter (p<0.001). At postpartum week 28, the rate of mother-to-child transmission was significantly lower in the TDF group than in the control group, both in the intention-to-treat analysis (5 vs 18 percent; p=0.007) and the per-protocol analysis (0 vs 7 percent; p=0.01).

The maternal and infant safety profiles were similar in the TDF group and the control group, including birth-defect rates (2 and 1 percent, respectively; p=1), although more mothers in the TDF group had an increase in the creatine kinase level. After the discontinuation of TDF, alanine aminotransferase elevations above the normal range occurred more frequently in mothers in the TDF group than in those in the control group (45 vs 30 percent; p=0.03). The maternal HBV serologic outcomes did not differ significantly between the groups.

FDA issues warning over loperamide heart risks

15 JUN 2016

The US Food and Drug Administration (FDA) has issued a warning that high doses of the antidiarrheal medication loperamide are associated with a risk of heart problems.

The FDA says that healthcare professionals should be aware that higher-than-recommended doses can cause serious cardiac events, including QT interval prolongation, Torsades de Pointes or other ventricular arrhythmias, syncope and cardiac arrest. It also encourages them to consider loperamide, also known by the brand name Imodium, as a possible cause of unexplained cardiac events.

Additionally, the US medicines regulator warns that the risk of serious heart problems can be increased by interactions between loperamide and other drugs, such as some antibiotics and antifungals.

A recent article in the Annals of Emergency Medicine[1] (online, 29 April 2016) highlighted a growing issue of loperamide abuse by people with opioid addiction. The drug, an opioid agonist, has no central nervous system effects at therapeutic doses, but at higher doses might induce euphoria.

The paper outlined two cases where patients had died after using supratherapeutic doses of the drug to manage symptoms of opioid withdrawal. Some people also use loperamide to attempt to self-treat opioid addiction, the authors say.

The FDA says that most reported cases of serious heart problems with loperamide involved doses much higher than the recommended dose. It advises healthcare professionals to counsel patients on the importance of taking only the recommended dose and the risk of cardiac adverse events, as well as potential drug interactions.

Loperamide has been authorised for use in the UK since 1975.

A spokesperson for the Medicines and Healthcare products Regulatory Agency, the UK medicines regulator, says: “We are aware of the safety warning issued by the FDA about the abuse and misuse of loperamide (Imodium). We will consider what implications this may have for UK public health.”

Nephrinuria as potential screening tool for preeclampsia

An elevated level of urinary nephrin (nephrinuria) may be associated with an increased risk of preeclampsia (PE), according to a study, suggesting that a certain cut-off can facilitate identification of women with greater PE risk.

Researchers investigated the feasibility of nephrinuria use to assess the risk of PE by enrolling 89 pregnant women without hypertension or significant proteinuria in pregnancy (SPIP). The number of urine samples obtained was 31 during the first trimester, 125 during the second, and 93 during the third. Outcomes were changes in nephrin:creatinine ratio (NCR) and protein:creatinine ratio (PCR). SPIP was defined as PCR >0.27.

PE occurred in 14 of the women. In this group of women, NCR positively correlated with PCR (correlation coefficient, 0.862; p<0.0001).

However, there were no significant changes in NCR even with marked increases in PCR among 75 women with normotensive pregnancies. This shows that the increase in nephrinuria over the physiological range of proteinuria in pregnancy was small.

The risk of later PE development was greater among asymptomatic women with NCR >122 ng/mg (95th centile value for 75 women with normotensive pregnancies) than among those with NCR ≤122 during both the second trimester (relative risk [RR], 5.93; 95 percent CI, 2.59 to 13.6; 60 vs 10 percent) and third trimester (RR, 13.5; 3.31 to 55; 75 vs 5.5 percent).

Nephrin is a protein that is predominantly found at the glomerular slit diaphragm of podocytes. Previous studies have reported that nephrin expression is reduced in kidney biopsy specimens from women with PE and in autopsy specimens from women who died from PE. The reduced expression may be linked to increased shedding of nephrin from podocytes.

The findings suggest that NCR is unlikely to increase in normal pregnancy despite the gradual increases in PCR, whereas both NCR and PCR increase gradually with advancing gestation in PE pregnancies, researchers said. This indicates that urinary NCR may prove more useful in identifying women who are at higher risk of PE compared with urinary PCR.

C-section preferable to vaginal delivery in acute fatty liver of pregnancy

11 Aug 2016

Caesarean delivery appears to be linked to better pregnancy outcomes in acute fatty liver of pregnancy (AFLP) compared with vaginal delivery, according to a meta-analysis of 80 studies.

“In cases of AFLP where the condition is identified, the termination of pregnancy is the only treatment available to achieve the most desirable outcomes for both the mother and foetus. However, the guidelines for selecting the delivery mode among women with AFLP are lacking,” the investigators said.

“At present, most doctors prefer to choose caesarean section (C-section) for AFLP patients based on their clinical experience rather than a further assessment of the risks.”

To evaluate the effect of C-section versus vaginal delivery on the maternal and perinatal outcomes, the investigators pooled data from studies involving 1,350 women with AFLP (mean age 25.2 years; mean gestational age 36 weeks; mean AFLP-to-delivery interval 8.14 days). Primary endpoints were maternal, perinatal, and neonatal mortality. Secondary endpoints included liver failure-associated complications, other organ injuries, obstetric haemorrhage, and infection.

C-section was associated with lower maternal and perinatal mortality risks compared with vaginal delivery (relative risk [RR], 0.56; 0.41 to 0.76; and RR, 0.52; 0.38 to 0.71, respectively). Meanwhile, neonatal mortality risk varied between the two delivery methods. [Sci Rep 2016;6:28826]

Complications and injuries—including disseminated intravascular coagulation, hypoglycaemia, ascites, encephalopathy, renal insufficiency, pancreatitis, and multiple organ dysfunction syndrome—as well as obstetric haemorrhage and infection did not differ significantly between C-section and vaginal delivery.

The protective effect of C-section on maternal mortality is multifactorial, the investigators said.

“The reduction in the risk may be associated with the maternal physical features since the differences in body size and pelvic structure will give rise to the different obstetrical indications and results of delivery mode in patients with AFLP. It may also be related to the severity of AFLP, as caesarean section may be more appropriate to terminate pregnancy in more severe cases,” they explained.

They also cited medical factors such as longer interval prior to delivery as a possible contributing factor to the increased mortality risk among women with AFLP.

“[B]ased on current evidence, caesarean section is the safest method of delivery and should be recommended to lower the risk of adverse pregnancy outcomes in AFLP. Nevertheless, additional optimally designed studies that consider the possible confounding factors could eventually provide a better, comprehensive understanding of the association between perinatal mortality and the mode of pregnancy termination in AFLP,” they concluded.


Rivaroxaban outperforms heparin, warfarin; tied to lower hospital visits, healthcare costs

13 Aug 2016

Treatment with rivaroxaban appears to be associated with reduced incidences of hospitalisations and outpatient visits among patients with deep vein thrombosis (DVT) compared with low-molecular-weight heparin (LMWH) and warfarin, according to a study.

Researchers followed adult patients with DVT who initiated treatment with rivaroxaban (n=512) or LMWH/warfarin (n=512) immediately after diagnosis. The number of hospitalisations for all causes and for venous thromboembolism (VTE), healthcare resource utilisation (ER, outpatient, and other visits), as well as healthcare and pharmacy costs were assessed at 1, 2, 3, and 4 weeks after the diagnosis and compared between the two treatment arms.

The rivaroxaban treatment arm showed significantly lower mean all-cause hospitalisation numbers over 1 week (0.012 vs 0.032; p=0.044) and 2 weeks (0.022 vs 0.048; p=0.040) compared with the LMWH/warfarin arm. The mean VTE-related hospitalisation numbers were also significantly lower in the rivaroxaban arm over 1 week (0.008 vs 0.028; p=0.020), 2 weeks (0.016 vs 0.042; p=0.020), and 4 weeks (0.034 vs 0.068; p=0.036).

In terms of all-cause and VTE-related outpatient visits, the mean numbers were markedly lower among patients in the rivaroxaban arm than among those in the LMWH/warfarin arm over 1, 2, 3, and 4 weeks (p<0.001 for all).

Meanwhile, all-cause and VTE-related ER and other visits were comparable between the two treatment groups over the first 4 weeks.

Rivaroxaban users reported lower mean all-cause total healthcare costs than LMWH/warfarin users over the first 2 weeks (week 1: US$2,332 vs $3,428; p<0.001; week 2: $3,108 vs $4,524; p<0.001). Similarly, mean costs associated with all-cause hospitalisations (weeks 1 and 2) and pharmacy (weeks 1 to 4) were significantly lower among rivaroxaban users. Costs related to ER visits (weeks 1 to 4), outpatient visits (weeks 1 to 4), or other visits (with the exception of week 1) did not differ among patients between the two treatment arms.

The findings suggest that rivaroxaban is superior to LMWH/warfarin, with advantages such as simplified care facilitating less healthcare resource utilisation.